
Explore telescopic denture materials, retention designs and lab workflows, with practical guidance on fit, fabrication and maintenance for dental practices.
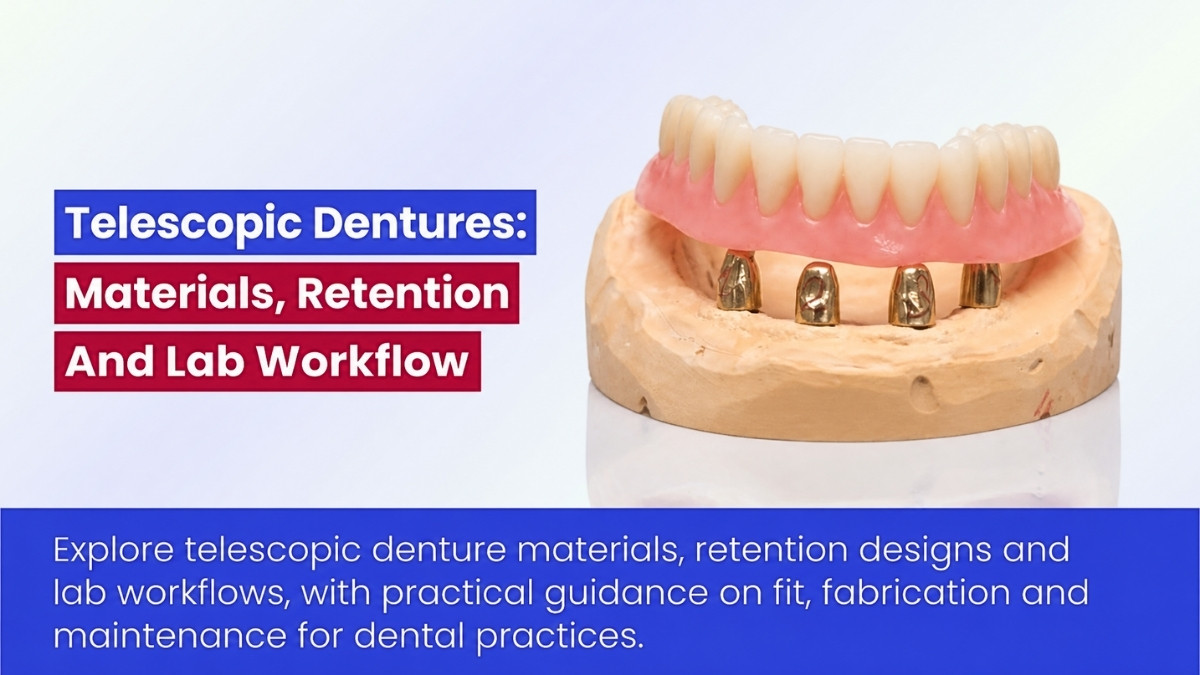
Table of contents [Show]
Telescopic dentures replace missing teeth without relying on visible clasps. Their stability comes from two precisely fitted crowns: an inner crown secured to a tooth or implant abutment, and an outer crown incorporated into a removable denture. For patients with a reduced dentition, this design can preserve useful supports while allowing access for cleaning.
That flexibility comes with a demanding workflow. A successful telescopic denture needs suitable abutments, an intentional retention design, accurate manufacturing and ongoing maintenance. This guide explains what dental practices should consider from treatment planning through laboratory delivery.
How do telescopic dentures work?
A telescopic denture is a double-crown-retained removable dental prosthesis. It has four main components:
- Primary crowns, or inner copings: These are secured to prepared natural teeth or attached to implant abutments.
- Secondary crowns, or outer copings: These fit over the primary crowns and are incorporated into the removable prosthesis.
- Framework: This connects the secondary crowns and supports the restoration.
- Denture base and artificial teeth: These replace missing teeth and, where needed, lost soft-tissue volume.
When the patient removes the denture, the primary crowns remain in the mouth. The relationship between the two sets of crowns helps resist dislodgement and guides the denture into position.
The main double-crown designs
“Telescopic denture” is often used as an umbrella term, but different double-crown systems do not retain or distribute loads in the same way. The distinction matters when prescribing and fabricating a restoration. A review of rigid and non-rigid systems explains these differences in greater detail.
| Design | How retention is achieved | Key consideration |
|---|---|---|
| Parallel-sided crowns | Close contact and friction between fitted surfaces | Sensitive to fit, contact area and surface finish |
| Conical or Konus crowns | Wedging as the outer crown seats on a tapered inner crown | Affected by taper, geometry and seating force |
| Clearance-fit systems | A defined space permits movement; another element may provide retention | Support and load distribution differ from rigid designs |
| Electroformed secondary copings | A thin, adapted coping is incorporated into a supporting framework | Accurate assembly and framework support are essential |
Retention, support and stability
Retention is only one part of performance. The prosthesis also needs support against movement toward the tissues and stability against rocking or rotation. More removal force is not automatically better: a denture that is difficult to remove can be hard for a patient to use and may place unfavorable forces on its supporting components.
When are telescopic dentures appropriate?
Telescopic dentures can be particularly useful when a patient has a small number of strategically positioned, restorable teeth. They may also be supported by implants or, in selected cases, by a combination of teeth and implants.
Common reasons to consider treatment
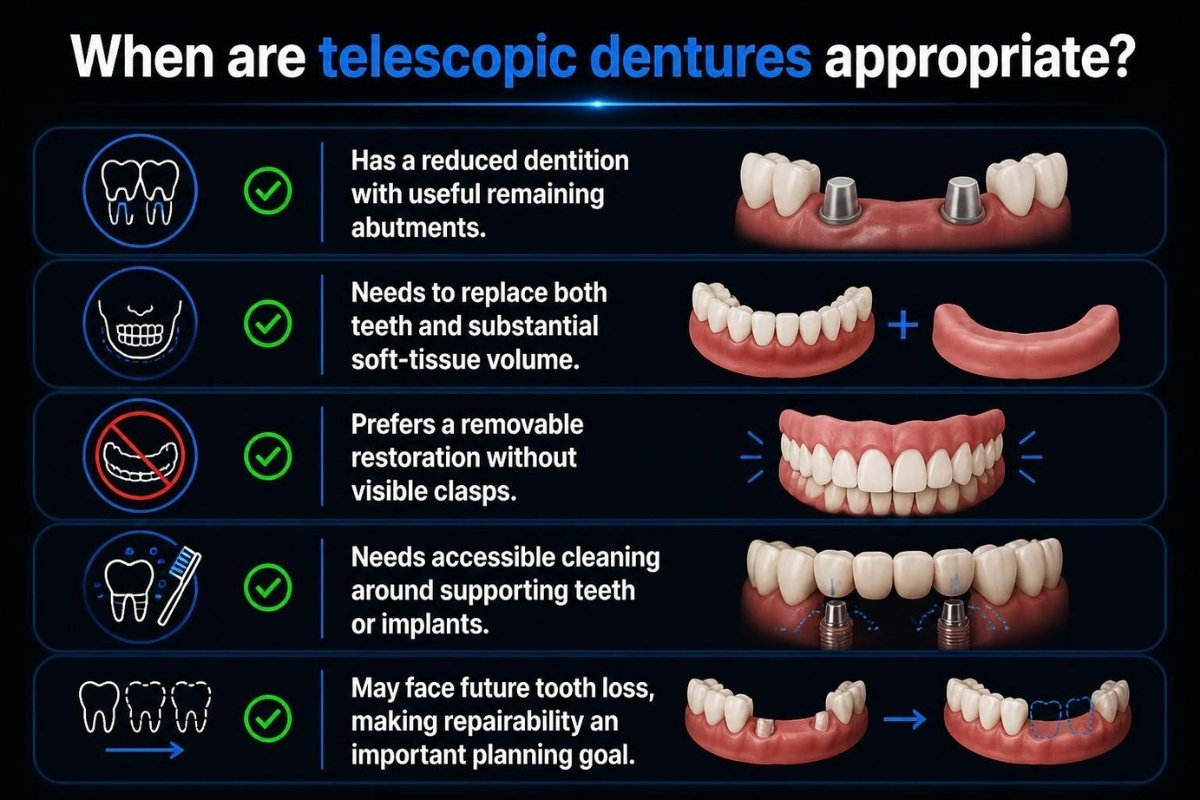
A clinician may consider a telescopic denture when the patient:
- Has a reduced dentition with useful remaining abutments.
- Needs to replace both teeth and substantial soft-tissue volume.
- Prefers a removable restoration without visible clasps.
- Needs accessible cleaning around supporting teeth or implants.
- May face future tooth loss, making repairability an important planning goal.
One advantage is potential adaptability. After an abutment is lost, some dentures can be modified rather than remade. Whether that is possible depends on the original design and the support that remains; it should be planned for, not promised.
What makes treatment less predictable?
The condition of the supporting structures matters more than the attachment’s sophistication. Untreated periodontal disease, active caries, poor plaque control, inadequate restorative space or abutments with poor structural prognosis can undermine the result. Patient dexterity matters too: the person must be able to insert, remove and clean the denture.
Treatment also has a biological cost. Natural-tooth abutments generally need preparation for primary crowns. Where a less invasive option can meet the patient’s needs, that trade-off deserves discussion.
Combining teeth and implants
For combined tooth–implant support, planning must account for the different mobility of periodontal-ligament-supported teeth and osseointegrated implants. Such a removable design should not be treated as mechanically equivalent to a rigid fixed tooth–implant bridge.
Materials and laboratory manufacturing
A telescopic interface must work as a complete material pairing, not merely as two individually suitable crowns. Crown geometry, manufacturing method, finishing and framework assembly all influence how the final denture seats and retains.
Materials used in telescopic dentures
| Material | Possible role | Laboratory consideration |
|---|---|---|
| Gold or other high-noble alloys | Inner and outer crowns | Established use and workability, but higher material cost |
| Cobalt–chromium | Copings and rigid frameworks | Stiffness is useful; accurate finishing is critical |
| Zirconia | Inner crowns in selected systems | Sintering, adjustment and polishing affect the interface |
| Electroformed gold | Thin secondary copings | Requires accurate incorporation into a supporting framework |
| PEEK or PEKK | Selected copings or framework components | Retention, wear, deformation and bonding need system-specific assessment |
| PMMA and dental composites | Bases, teeth and facings | Bond quality and repairability require control |
Newer materials can broaden design options, but laboratory retention tests do not establish long-term clinical superiority. A 2023 material-pairing study examined retention after repeated insertion and removal; its findings should be interpreted in the context of the specific materials and test conditions.
Why the workflow requires close coordination
Several individually well-fitting crowns must also work together. A small error in the recorded position of one coping can prevent a multi-abutment denture from seating correctly.
- Planning: Confirm abutment prognosis, distribution, available space, occlusion, hygiene access and a strategy for possible abutment loss.
- Prescription: Specify the double-crown design, materials, intended retention approach and framework requirements. “Make telescopes” leaves too much undefined.
- Position recording: Transfer the spatial relationship of the primary crowns using an appropriate impression, transfer, scan or hybrid method.
- Fit verification: Check individual coping fit and combined seating before completing the prosthesis.
- Framework assembly: Confirm rigidity, passive seating, adequate support for bases and facings, and access for cleaning.
- Final assessment: Evaluate seating, retention, occlusion and the patient’s ability to handle the denture.
Conventional, digital and hybrid manufacturing
CAD/CAM can help define geometry and reproduce components, while conventional milling, electroforming and hybrid methods remain relevant. No method removes the need for clinical verification. In particular, a visually complete digital scan does not by itself prove that multiple crowns will seat together.
Clinical outcomes, complications and maintenance
Telescopic dentures are an established treatment option, but there is no single success rate that applies to every design or patient. Studies vary in abutment condition, materials, follow-up and what they define as failure.
What the clinical evidence shows
A systematic review by Verma and colleagues found variation across tooth- and implant-retained double-crown prostheses. In a more recent practice-based retrospective study of 213 prostheses in 174 patients, estimated prosthesis survival was 94% at two years and 86% at five years. The estimated probability of remaining free from prosthesis-related complications at five years was 80%.
Those figures illustrate an important distinction: a denture may remain usable while still needing repair or maintenance. They are results from one cohort, not a prediction for an individual patient.
A 2026 retrospective cohort study compared telescopic-crown-retained dentures with root-cap-retained overdentures and evaluated survival, complications and maintenance as separate outcomes. Those endpoints should remain separate when discussing results with patients.
What needs monitoring?
Biological issues can include caries around coping margins, periodontal or peri-implant inflammation, endodontic problems and abutment fracture. Technical issues can include primary-crown decementation, changes in retention, coping debonding, fractures, and the need for relining or occlusal adjustment.
Recall intervals should reflect the patient’s disease risk and prosthesis complexity. At each review, the practice should assess the tissues and abutments alongside seating, retention, wear, hygiene and the patient’s ability to remove and clean the denture.
When a primary crown comes loose
If a primary crown comes out inside the prosthesis, simply recementing it may miss the cause. The tooth, crown fit, insertion path and denture seating need evaluation first. Similarly, unplanned grinding of an inner crown can permanently change retention.
Quality standards and the practice–laboratory handoff

Relevant standards can inform material selection and quality systems, but no single ISO certificate establishes the clinical performance of an entire telescopic denture. Depending on the components used, relevant standards may include ISO 22674 for metallic dental materials, ISO 6872 for dental ceramics, ISO 20795-1 for denture-base polymers and ISO 13485 for medical-device quality-management systems. The applicable edition and scope should be checked in the official ISO catalogue.
Regulatory language should be equally precise. A quality-management certification is not proof that a particular primary–secondary crown pairing will deliver suitable retention. Likewise, compliance with applicable U.S. requirements should not be described as blanket FDA approval of a laboratory or every custom-made denture.
What to document for an outsourcing partner
For practices working with a dental laboratory outsourcing partner, a useful case handoff records the specified system and materials, abutment positions, seating verification, retention assessment, material traceability, and adjustment or repair instructions. Those details make the delivered prosthesis easier to evaluate and maintain.
At XDENT LAB, telescopic dentures fit within a broader removable-prosthetics conversation: the restoration must be planned as a precise, maintainable system shared between clinician and laboratory. The most valuable specification is not simply the name of a material. It is the validated combination of materials, geometry, manufacturing, finishing, assembly and maintenance protocol.
Frequently asked questions about telescopic dentures
Are telescopic dentures fixed or removable?
They are removable. The primary crowns stay on the supporting teeth or implant abutments when the patient takes out the denture.
Are telescopic dentures the same as clasp dentures?
No. Telescopic designs primarily use fitted double crowns for retention, although a particular treatment design may incorporate other components.
Can a telescopic denture be repaired after an abutment is lost?
Sometimes. Repair depends on the denture’s original design and whether the remaining abutments provide adequate support.
How long do telescopic dentures last?
Lifespan varies with abutment health, design, hygiene and maintenance. Prosthesis survival does not mean the denture will need no adjustments or repairs during that time.
Key takeaway
Telescopic dentures are not simply clasp-free dentures. They are precision restorations whose success depends on sound patient selection, deliberate double-crown design, accurate laboratory execution and lifelong follow-up.
About XDENT LAB:
We are experts in Lab-to-Lab Full Service from Vietnam, with the signature services of Removable, meet U.S. market standards, FDA-registered, ISO 13485-certified. Founded in 2017, from local root to global reach, we scale with 2 Factories with over 100+ employees.

Our Commitments Built on “Trusted. Commitment. Quality”
- Commit to Large-Scale Manufacturing, high volume, remake rate < 1%.
- Commit to 5-Year Warranty
- Commit to Competitive Price
XDENT LAB | A Trusted Lab-to-Lab Service from Vietnam
Share this post:
Related Posts

Materials used in fixed prosthodontics, from zirconia and lithium disilicate to alloys, with guidance on indications, bonding, workflows, and selection.
Learn how implant-retained overdentures rely on clinical planning, attachment selection, and laboratory QC for stable, predictable removable outcomes.
Learn how tooth-supported overdentures rely on careful clinical planning, abutment selection, attachments, and laboratory QC for stable, predictable results.

