
Explore cast metal framework partial dentures, including design principles, material selection, lab workflow, fit, hygiene, and long-term clinical performance.
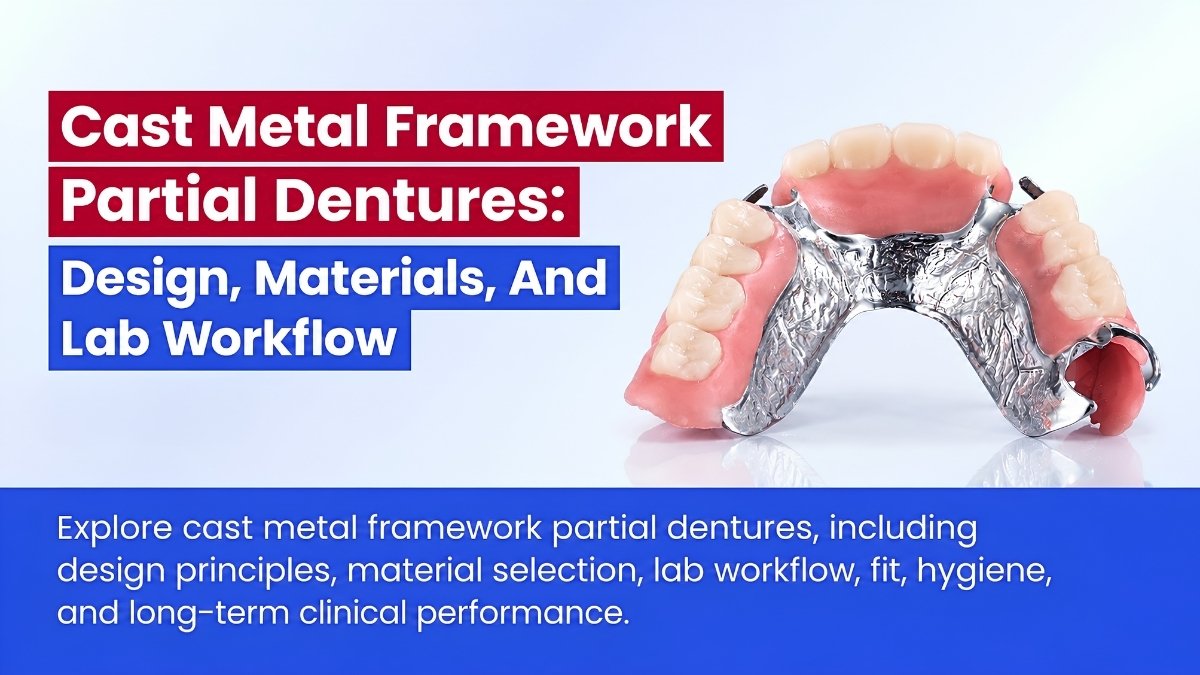
Table of contents [Show]
- Definition and clinical role
- Why cast metal framework RPDs matter
- Difference between acrylic partial denture and cast metal framework RPD
- Main components of cast metal framework partial dentures
- Major connectors
- Rests and rest seats
- Direct retainers: Clasps and attachments
- Indirect retainers
- Kennedy classification and cast framework design
- Materials used for cast metal framework RPDs
- Conventional laboratory workflow
- Digital workflow and additive manufacturing
- Clinical-laboratory communication
- Framework design principles
- Tooth preparation for cast partial dentures
- Impression requirements
- Fit and try-in
- Denture base and tooth arrangement
- Common complications
- Maintenance and follow-up
- International standards and materials compliance
- Laboratory quality control checklist
- Why this matters for XDENT LAB
- Key takeaways
Cast metal framework partial dentures are one of the most established and technically demanding treatments in removable prosthodontics. They sit at the intersection of biomechanics, materials science, tooth preservation, periodontal protection, surveying, framework design, and laboratory casting or digital metal manufacturing. When well designed, they are thin, strong, stable, hygienic, and long-lasting. When poorly designed, they become plaque-retentive metal sculptures with clasps, and patients notice.
For dental practices looking to ensure quality and consistency, cast metal framework removable partial dentures remain highly relevant because they offer a durable, conservative, and economically practical solution for partial edentulism. Their long-term success depends on coordinated clinical preparation, accurate laboratory execution, clear prescription design, and disciplined quality control.
Definition and clinical role
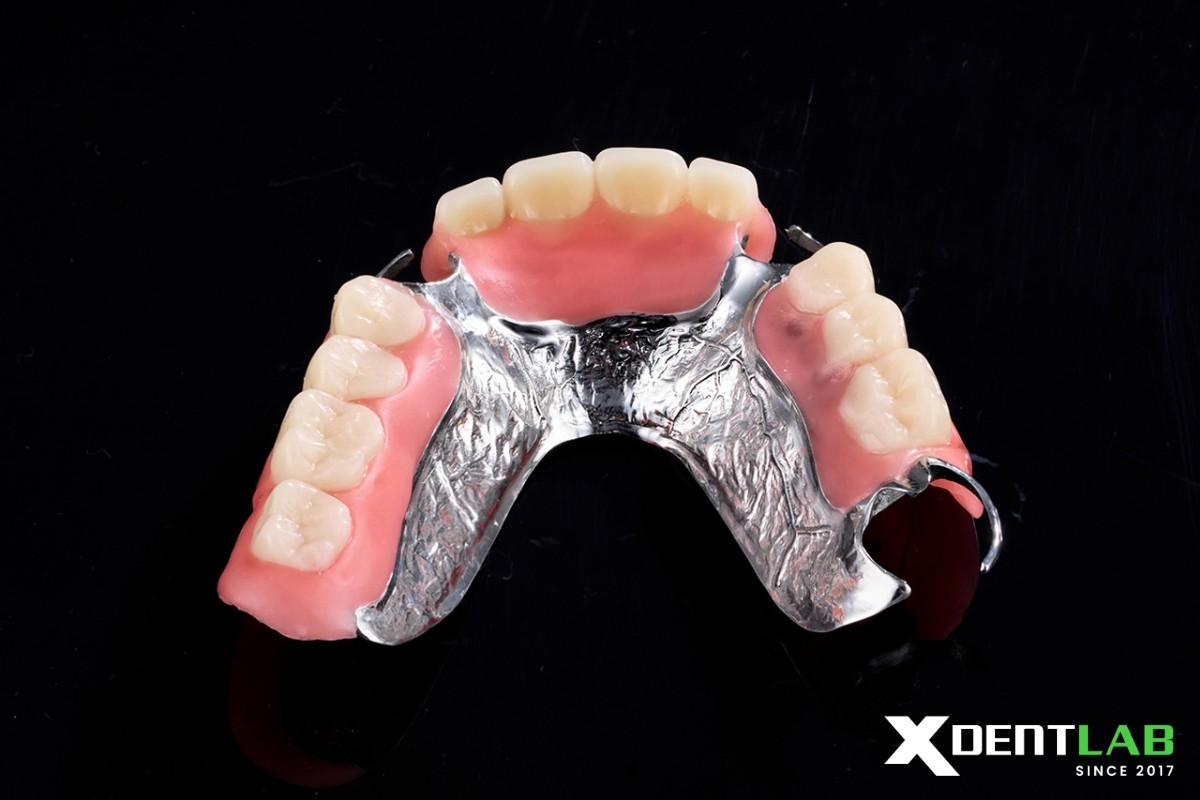
A cast metal framework removable partial denture, often called a cast partial denture, cobalt-chromium partial denture, or metal framework RPD, is a removable prosthesis used to replace missing teeth when some natural teeth remain.
The denture is supported and retained by a rigid metal framework that rests partly on the remaining teeth and partly on the oral mucosa.
Core definition
A cast metal framework partial denture usually consists of:
- A cast metal framework
- Acrylic resin denture bases
- Artificial denture teeth
- Occlusal rests
- Clasps or precision attachments
- Major and minor connectors
- Meshwork or lattice retention for acrylic resin
- Guiding plates and reciprocal components
These prostheses are designed to distribute forces between abutment teeth and supporting tissues while restoring function, speech, and esthetics.
Cast framework partial dentures remain clinically important because they can provide a durable and conservative solution for partially edentulous patients.

Main advantages
- More rigid than acrylic partial dentures
- Thinner and less bulky
- Better long-term stability
- Better force distribution
- More hygienic when properly designed
- More fracture-resistant than all-acrylic partials
- Can preserve remaining teeth when designed correctly
- Can be repaired or modified in selected cases
- More economical than many implant-supported fixed options
- Useful when implants or fixed bridges are contraindicated
Common clinical uses
| Clinical situation | Why cast framework RPD may be used |
|---|---|
| Multiple missing teeth | Replaces several teeth economically |
| Distal-extension edentulism | Restores free-end saddles where fixed bridges are difficult |
| Long-span edentulous areas | Avoids excessive fixed bridge span |
| Periodontally reduced dentition | Can splint and distribute forces if carefully designed |
| Implant contraindication | Provides non-surgical replacement |
| Financial limitation | Lower cost than implant rehabilitation |
| Transitional treatment | Stabilizes function before future definitive treatment |
| Complex partial edentulism | Flexible design options |
Acrylic partial dentures and cast metal framework RPDs both replace missing teeth, but their biomechanical behavior is very different.
| Feature | Acrylic partial denture | Cast metal framework RPD |
|---|---|---|
| Main framework | Acrylic resin | Cast or milled metal alloy |
| Rigidity | Lower | Higher |
| Thickness | Bulkier | Thinner |
| Support | Mostly tissue-supported | Tooth- and tissue-supported |
| Longevity | Often temporary or interim | Long-term definitive option |
| Hygiene | Can be more plaque-retentive | Better if well designed |
| Adjustment or repair | Easier | More complex |
| Cost | Lower | Higher |
| Precision | Lower | Higher |
| Clinical indication | Transitional or simple cases | Definitive partial denture cases |
Acrylic partials are useful, but a properly designed cast metal RPD is generally a more controlled, more durable, and more biomechanically sound prosthodontic appliance.
A cast partial denture is not just metal plus teeth. Each component has a biomechanical purpose.
Core components
| Component | Function |
|---|---|
| Major connector | Joins parts of the framework across the arch |
| Minor connector | Connects rests, clasps, and denture base to major connector |
| Rests | Provide vertical support and prevent tissue-ward movement |
| Rest seats | Tooth preparations that receive rests |
| Direct retainers | Clasps or attachments that resist dislodgement |
| Indirect retainers | Help resist rotational movement in distal-extension cases |
| Guiding plates | Control path of insertion and improve stability |
| Denture base retentive mesh | Retains acrylic resin saddle |
| Denture base | Supports artificial teeth over edentulous ridge |
| Artificial teeth | Restore mastication, speech, and esthetics |
| Reciprocal arms or plates | Counteract clasp forces during insertion and removal |
Practical principle
Every part of the framework should do one of five things:
- Support the denture
- Stabilize the denture
- Retain the denture
- Connect components
- Replace missing tissue or teeth
If a metal component does none of these things, it is probably just decorative trouble.
Major connectors
The major connector is the main structural unit connecting one side of the arch to the other.
Maxillary major connectors
Common maxillary designs include:
- Palatal strap
- Anterior-posterior palatal strap
- Palatal plate
- U-shaped or horseshoe connector
- Complete palatal coverage
- Single palatal bar, less commonly used due to rigidity concerns
Mandibular major connectors
Common mandibular designs include:
- Lingual bar
- Lingual plate
- Sublingual bar
- Continuous bar or Kennedy bar
- Labial bar, used only in special cases
Design requirements
A major connector should be:
- Rigid
- Hygienic
- Comfortable
- Away from gingival margins when possible
- Smooth and polished
- Non-irritating to oral tissues
- Properly relieved where needed
- Strong enough to resist flexure
Why rigidity matters
A flexible major connector allows harmful movement and torque on abutment teeth. Cobalt-chromium is favored because it allows relatively thin yet rigid connector designs.
Rests and rest seats
Rests are essential because they provide vertical support.
Without rests, an RPD can sink into soft tissue and damage the periodontium.
Types of rests
| Rest type | Location / use |
|---|---|
| Occlusal rest | Posterior teeth |
| Cingulum rest | Canines or incisors |
| Incisal rest | Anterior teeth, less esthetic |
| Embrasure rest | Between adjacent posterior teeth |
| Onlay rest | Extensive occlusal coverage in selected cases |
Functions of rests
- Prevent tissue-ward displacement
- Direct forces along the long axis of abutment teeth
- Maintain clasp position
- Prevent food impaction under the framework
- Improve stability
- Support indirect retainers
- Preserve periodontal health when designed well
Rest seat preparation
Rest seats should be prepared by the dentist, not discovered accidentally by the framework during insertion. Clear rest seat preparation is one of the most important clinical responsibilities in cast partial denture treatment.
Direct retainers resist removal of the denture.
Common clasp types
| Clasp type | Common use |
|---|---|
| Circumferential or Akers clasp | Tooth-supported partial dentures |
| RPI system | Distal-extension RPDs |
| RPA clasp | Alternative distal-extension design |
| I-bar clasp | Esthetic approach arm clasp |
| T-bar or Y-bar clasp | Selected undercut designs |
| Ring clasp | Tilted molars |
| Back-action clasp | Selected posterior cases |
| Embrasure clasp | No edentulous space adjacent to abutment |
| Wrought wire clasp | Stress-breaking flexibility, often for distal extensions |
RPI system
The RPI clasp system includes:
- R: Mesial rest
- P: Proximal plate
- I: I-bar retainer
It is commonly used in distal-extension cases because it helps reduce harmful torque on abutment teeth during tissue-ward movement of the denture base.
Some cast framework RPDs use attachments instead of visible clasps.
Examples include:
- Intracoronal attachments
- Extracoronal attachments
- Stud attachments
- Bar attachments
- Magnetic attachments
- Telescopic crowns
Advantages
- Improved esthetics
- Better retention
- Reduced visible clasping
Limitations
- Higher cost
- More technique-sensitive
- Requires more tooth preparation
- Needs maintenance
- Attachment wear over time
Indirect retainers
Indirect retainers help prevent rotation of distal-extension partial dentures away from the tissues.
Common indirect retainer sites
- Cingulum rest on canine
- Occlusal rest on premolar
- Incisal rest on anterior tooth
- Auxiliary rest away from fulcrum line
When they are most important
- Kennedy Class I cases
- Kennedy Class II cases
- Long distal-extension saddles
- Cases with resilient mucosa
- Cases with high dislodging forces
Basic principle
The indirect retainer should be placed as far as practical from the fulcrum line to increase resistance to rotation.
Kennedy classification and cast framework design
The Kennedy classification is commonly used to classify partially edentulous arches.
Kennedy classes
| Class | Description | RPD design challenge |
|---|---|---|
| Class I | Bilateral posterior edentulous areas | Distal-extension rotation |
| Class II | Unilateral posterior edentulous area | Unilateral distal-extension rotation |
| Class III | Bounded edentulous area | Tooth-supported, usually more stable |
| Class IV | Single anterior edentulous area crossing midline | Esthetics and anterior support |
Design implications
- Class I and II cases require careful control of rotation, indirect retention, broad tissue support, and stress distribution.
- Class III cases are generally more tooth-supported and mechanically favorable.
- Class IV cases require strong esthetic planning, indirect retention, and careful anterior tooth arrangement.
Framework material selection affects rigidity, casting behavior, adjustment, corrosion resistance, and long-term function.
Main framework materials
| Material | Use / characteristics |
|---|---|
| Cobalt-chromium alloy | Most common framework material |
| Nickel-chromium alloy | Historically used, allergy concerns |
| Titanium | Lightweight, biocompatible, more technique-sensitive |
| Gold alloy | Excellent properties but costly and less common |
| Stainless steel or wrought wire | Clasps or auxiliary components, not usually full cast framework |
Cobalt-chromium
Cobalt-chromium is the dominant material for cast partial denture frameworks.
Advantages
- High rigidity
- High strength
- Corrosion resistance
- Lower density than gold
- Can be cast thin
- Good long-term durability
- Cost-effective compared with noble alloys
Limitations
- Technique-sensitive casting
- Difficult adjustment
- Brittle compared with wrought wire in clasp arms
- Requires accurate design
- Polishing requires skill
- Metal sensitivity is possible, though nickel is the more common concern
Titanium
Titanium frameworks are less common but valuable in selected cases.
Advantages
- Excellent biocompatibility
- Lightweight
- Corrosion resistance
- Useful for metal-sensitive patients
Limitations
- Casting is technically difficult
- Requires special equipment
- More expensive
- Framework adjustment can be challenging
Conventional laboratory workflow
Traditional cast framework fabrication is a highly structured laboratory process.
Workflow
Prescription and master impression received
→ Cast poured
→ Surveying
→ Design verification
→ Blockout
→ Duplication
→ Refractory cast fabrication
→ Wax pattern framework
→ Spruing
→ Investing
→ Burnout
→ Casting
→ Divesting
→ Finishing
→ Electrolytic polishing or mechanical polishing
→ Framework fit verification
→ Clinical try-in
→ Jaw relation or tooth setup
→ Wax try-in
→ Processing acrylic base
→ Finishing and polishing
→ Final QC
→ Delivery
Key laboratory steps
Surveying determines:
- Path of insertion
- Height of contour
- Undercut location
- Guide planes
- Clasp position
- Blockout requirements
- Framework design feasibility
2. Blockout
Blockout prevents the framework from locking onto undercuts.
Types include:
- Parallel blockout
- Relief blockout
- Arbitrary blockout
- Shaped blockout
- Tissue relief
3. Duplication
A duplicate refractory cast is made so the wax framework can be created and cast without damaging the master cast.
4. Wax-up
The framework is waxed on the refractory cast using preformed wax patterns or custom wax design.
5. Casting
The framework is cast using cobalt-chromium or another alloy.
6. Finishing and polishing
The finished framework must be smooth, accurate, and tissue-friendly.
Digital workflow and additive manufacturing
Modern cast metal framework RPDs can also be produced digitally.
Digital workflow
Intraoral scan or model scan
→ Digital surveying
→ CAD framework design
→ 3D printed resin pattern or direct metal printing
→ Casting or selective laser melting
→ Finishing and polishing
→ Framework try-in
→ Tooth setup and acrylic processing
Digital manufacturing methods
| Method | Description |
|---|---|
| CAD plus printed resin pattern plus casting | Digital design with conventional casting |
| Selective laser melting or SLM | Direct metal additive manufacturing |
| Milling wax or resin pattern | Milled pattern later cast |
| Direct milling metal | Less common for complex RPD frameworks |
Digital advantages
- Repeatable design
- Digital storage
- Faster duplication
- Reduced manual wax-up variability
- Digital surveying
- Easier design communication
- Potential for improved fit
- Efficient remakes
Digital limitations
- Requires accurate scan data
- Software design skill is essential
- Post-processing remains critical
- Metal printing parameters affect fit and strength
- Polishing is still labor-intensive
- Design errors can be reproduced perfectly, which is efficient but not always helpful
Clinical-laboratory communication
Cast framework RPDs are highly dependent on prescription quality.
What the dentist should provide
- Clear RPD design
- Kennedy classification
- Tooth numbers to replace
- Abutment teeth
- Rest seat locations
- Clasp design
- Major connector design
- Guide plane preparations
- Occlusal scheme notes
- Shade and mold selection
- Special tissue relief instructions
- Opposing arch information
- Surveyed cast or digital design when possible
Why this matters
In many jurisdictions, denture design is a clinical responsibility. The dental technician can advise, but the dentist must prescribe the design because the design directly affects teeth, soft tissues, and long-term oral health.
Framework design principles
A cast metal RPD should be designed around biomechanical control.
Essential principles
1. Support
Prevent tissue-ward movement using rests and broad denture base coverage.
2. Retention
Use clasps, guide planes, attachments, and undercuts appropriately.
3. Stability
Resist horizontal movement through rigid components, guide plates, and proper base adaptation.
4. Reciprocation
Counteract clasp forces with reciprocal arms or plates.
5. Bracing
Resist lateral forces.
6. Indirect retention
Control rotation in distal-extension cases.
7. Stress distribution
Avoid overloading abutment teeth or residual ridges.
8. Hygiene
Keep margins cleanable and avoid unnecessary tissue coverage.
9. Rigidity
Prevent harmful flexure of the framework.
10. Comfort
Avoid bulky or irritating components.
Tooth preparation for cast partial dentures
Successful cast framework RPDs often require mouth preparation before impression.
Common preparations
- Occlusal rest seats
- Cingulum rest seats
- Guide planes
- Enameloplasty
- Surveyed crowns if needed
- Recontouring undercuts
- Periodontal therapy
- Caries control
- Replacement of defective restorations
- Crown preparation for precision attachments if indicated
Rest seat design principles
| Rest seat type | Design considerations |
|---|---|
| Occlusal rest seat | Spoon-shaped, rounded, directs force along tooth axis |
| Cingulum rest seat | Prepared in enamel or restoration, avoids sliding |
| Incisal rest seat | Less esthetic, used when needed |
| Embrasure rest seat | Requires preparation on adjacent teeth to avoid wedging |
Guide planes
Guide planes improve:
- Path of insertion
- Stability
- Frictional resistance
- Clasp effectiveness
- Denture seating
- Reciprocation
Impression requirements
Accurate impressions are essential because framework fit begins long before metal is cast.
Tooth-supported cases
For Kennedy Class III cases, a high-quality definitive impression may be sufficient.
Distal-extension cases
Kennedy Class I and II cases are more difficult because the prosthesis is supported by both teeth and movable mucosa.
Additional techniques may include:
- Altered cast impression
- Functional impression of distal extension
- Selective pressure impression
- Border molding
- Secondary impression after framework try-in
Why altered cast technique matters
In distal-extension RPDs, teeth and mucosa move differently under load. The altered cast technique helps improve support and reduce rotation by recording edentulous tissues under more functional conditions.
Fit and try-in
A cast framework should be tried in before tooth setup and acrylic processing.
Framework try-in checks
- Complete seating
- Rest fit
- Major connector adaptation
- Clasp engagement
- Tissue relief
- Stability
- No rocking
- Guide plane contact
- Occlusal clearance
- Patient comfort
- Esthetics of clasp display
Common framework fit problems
| Problem | Possible cause |
|---|---|
| Framework does not seat | Undercut not blocked out, casting distortion, rest interference |
| Rocking framework | Inaccurate cast, poor fit, distorted framework |
| Tight clasp | Incorrect undercut selection or finishing |
| Loose clasp | Under-engagement, casting or polishing error |
| Tissue impingement | Insufficient relief |
| High rest | Inaccurate rest seat or casting |
| Major connector discomfort | Poor adaptation or excessive thickness |
Denture base and tooth arrangement
After framework approval, acrylic bases and denture teeth are added.
Denture base requirements
- Accurate tissue adaptation
- Adequate extension
- Proper support
- Smooth tissue surface
- Strong attachment to metal mesh
- No sharp resin-metal junctions
- Easy hygiene access
Artificial tooth selection
Consider:
- Shade
- Mold
- Occlusion
- Ridge relationship
- Opposing dentition
- Available space
- Esthetic demands
- Wear resistance
- Acrylic versus composite denture teeth
Occlusion
RPD occlusion must be designed to reduce harmful forces.
Important points include:
- Stable bilateral contacts where appropriate
- No premature contacts on denture teeth
- Avoid heavy contacts on distal extensions
- Harmonize with the opposing arch
- Adjust after insertion
- Recheck after tissue settling
Common complications
Complications are usually mechanical, biological, or design-related, and many are preventable.
Biological complications
- Caries on abutment teeth
- Periodontal inflammation
- Gingival trauma
- Plaque accumulation
- Soft tissue soreness
- Residual ridge resorption
- Food impaction
- Abutment mobility
- Root caries in elderly patients
Mechanical complications
- Clasp fracture
- Framework fracture
- Acrylic base fracture
- Tooth debonding
- Loss of retention
- Distortion from adjustment
- Wear of denture teeth
- Rest fracture
- Connector fatigue
| Design error | Likely consequence |
|---|---|
| No rests | Tissue sinking and gingival trauma |
| Flexible major connector | Torque and instability |
| Poor clasp position | Poor retention or tooth damage |
| No indirect retention | Distal-extension rotation |
| Overcovered gingiva | Plaque and inflammation |
| Poor base extension | Instability and soreness |
| Inadequate reciprocation | Tooth movement during insertion or removal |
Maintenance and follow-up
Cast framework RPDs require maintenance. Delivery is not the final step in care.
Clinical follow-up schedule
- 24 to 48 hours after insertion
- 1 week
- 1 month
- Every 6 months or based on risk
At recall visits, evaluate
- Tissue health
- Plaque control
- Caries risk
- Periodontal status
- Abutment mobility
- Clasp retention
- Framework fit
- Denture base adaptation
- Occlusion
- Denture hygiene
- Patient comfort
- Need for reline or adjustment
Patient instructions
Patients should be told to:
- Remove the denture at night unless instructed otherwise
- Clean the denture daily
- Brush abutment teeth carefully
- Avoid bending clasps
- Avoid abrasive cleaners
- Store the denture safely
- Return for adjustments rather than self-adjusting
- Attend recall visits
International standards and materials compliance
Cast metal framework partial dentures are custom dental devices and should be manufactured under controlled conditions.
Relevant standards
| Standard / framework | Relevance |
|---|---|
| ISO 13485 | Quality management system for medical devices |
| ISO 22674 | Metallic materials for fixed and removable dental restorations |
| ISO 10993 series | Biological evaluation of medical devices |
| ISO 7405 | Biological evaluation of dental materials |
| ISO 20795 series | Denture base polymers |
| Local medical device regulations | Country-specific dental appliance requirements |
| Manufacturer IFU | Alloy processing, casting, polishing, and acrylic bonding instructions |
Laboratory documentation should include
- Dentist prescription
- Patient or case identifier
- Framework alloy
- Alloy lot number
- Acrylic resin lot number
- Denture tooth brand and shade
- Design record
- Survey path
- Casting or manufacturing record
- Finishing or polishing record
- Final QC record
- Delivery date
Laboratory quality control checklist
A cast framework RPD needs rigorous QC before delivery.
CAST METAL FRAMEWORK RPD QC CHECKLIST
Case ID: ___________________________
Dentist / Clinic: __________________
Patient ID: ________________________
Arch: Maxillary / Mandibular
Kennedy Class: _____________________
Framework Alloy: ___________________
Alloy Lot Number: __________________
Date: ______________________________
DESIGN VERIFICATION
[ ] Prescription reviewed
[ ] Kennedy classification confirmed
[ ] Major connector correct
[ ] Minor connectors correct
[ ] Rest locations correct
[ ] Clasp design correct
[ ] Indirect retainers included if needed
[ ] Mesh/lattice areas correct
[ ] Tissue relief/blockout completed
FRAMEWORK FIT
[ ] Framework seats fully
[ ] No rocking
[ ] Rests fit accurately
[ ] Major connector adapted
[ ] Guide plates contact correctly
[ ] Clasps engage correct undercuts
[ ] Tissue relief adequate
[ ] No sharp internal areas
METAL QUALITY
[ ] No casting porosity
[ ] No incomplete casting
[ ] No cracks
[ ] No nodules interfering with fit
[ ] Framework thickness adequate
[ ] Clasps not over-polished
[ ] Metal polished smooth
[ ] Tissue-contact areas smooth
ACRYLIC / TEETH
[ ] Tooth shade and mold verified
[ ] Tooth setup follows prescription
[ ] Acrylic processed properly
[ ] Resin-metal junction smooth
[ ] No porosity in acrylic
[ ] Base extension appropriate
[ ] Denture teeth securely retained
OCCLUSION AND FINISH
[ ] Occlusion checked
[ ] No premature heavy contacts
[ ] Borders smooth
[ ] No sharp edges
[ ] Final polish completed
[ ] Denture cleaned and disinfected
FINAL RELEASE
[ ] Material lot numbers recorded
[ ] QC approved
[ ] Case packed securely
[ ] Instructions included if needed
Technician: ________________________
QC Inspector: ______________________
Why this matters for XDENT LAB
Cast metal framework partial dentures align closely with XDENT LAB’s strength in removable prosthodontics because they demand the kind of repeatable technical control that distinguishes an experienced lab from a merely busy one.
Strategic relevance for XDENT LAB
- Lab-to-lab removable prosthetic workflows
- Cobalt-chromium framework expertise
- Conventional and digital RPD production support
- Material traceability
- FDA and ISO-aligned quality systems
- Skilled surveying, design, and finishing
- Vietnam dental lab scalability for consistent case output
- Structured QC for framework fit, clasp design, base adaptation, and final polish
For dental practices seeking quality and consistency, cast framework partial dentures are one of the clearest examples of how laboratory discipline directly affects comfort, hygiene, longevity, and protection of the remaining dentition.
Key takeaways
Cast metal framework partial dentures are definitive removable prostheses built around a rigid metal framework, most commonly cobalt-chromium.
- They are stronger, thinner, and more stable than acrylic partial dentures.
- Their success depends heavily on design, especially rests, clasps, major connectors, indirect retainers, and guide planes.
- Cobalt-chromium is the most common framework alloy because it is strong, rigid, corrosion-resistant, and suitable for thin frameworks.
- Rest seats and guide planes must be prepared clinically to achieve proper support and path of insertion.
- Dentist-laboratory communication is critical because incomplete prescriptions compromise design quality and long-term oral health.
- Distal-extension cases require special biomechanical control because the denture is supported by both teeth and mucosa.
- Digital RPD workflows are expanding, especially through CAD design, printed patterns, and selective laser melting frameworks.
- Framework fit, polish, hygiene access, and recall maintenance determine long-term success.
A well-made cast metal framework RPD is not simply a removable denture. It is a carefully engineered prosthesis designed to protect remaining teeth, restore function, and serve the patient for years.
About XDENT LAB:
We are experts in Lab-to-Lab Full Service from Vietnam, with the signature services of Removable, meet U.S. market standards, FDA-registered, ISO 13485-certified. Founded in 2017, from local root to global reach, we scale with 2 Factories with over 100+ employees.

Our Commitments Built on “Trusted. Commitment. Quality”
- Commit to Large-Scale Manufacturing, high volume, remake rate < 1%.
- Commit to 5-Year Warranty
- Commit to Competitive Price
XDENT LAB | A Trusted Lab-to-Lab Service from Vietnam
Share this post:
Related Posts
Not all occlusal rests are the same. Here is what distinguishes the extended, interproximal, internal types, and the clinical situations each one is designed for.
Explore lab-to-lab workflow and QC for implant-supported fixed prostheses, from fit and materials to retrievability, hygiene design, and consistency.

Explore lab workflow and quality standards for inlays, onlays, and overlays to improve fit, occlusion, durability, and restorative consistency.

